
When is shoulder replacement considered?
Shoulder replacement is considered when arthritis or irreparable rotator cuff damage causes pain and loss of function that no longer respond to non-surgical care — night pain, difficulty dressing, reaching and lifting, despite medication, physiotherapy and injections.
Types of shoulder replacement
There are three main options, and the state of your rotator cuff — more than your age — usually decides between them.
Anatomic total shoulder replacement
The worn ball and socket surfaces are replaced, reproducing normal anatomy. Most appropriate for osteoarthritis with an intact rotator cuff, where it gives the most natural shoulder mechanics and the best rotation.
Reverse total shoulder replacement
The ball and socket positions are switched, allowing the deltoid muscle to power the arm when the rotator cuff is deficient. The preferred option for cuff tear arthropathy, irreparable cuff tears, and many complex fractures in older patients.
Pyrocarbon hemiarthroplasty
Only the ball is replaced, with a pyrocarbon head, and your own socket is preserved. Aimed at active patients with a working rotator cuff, avoiding the plastic socket that is the usual long-term weak point. Suitability rests on activity level and bone quality rather than age alone.
Dr Melsom will recommend the design that fits your anatomy, cuff status and goals.
Blueprint 3D shoulder planning
Blueprint planning can be used for both anatomic total shoulder replacement and reverse shoulder replacement. It helps Dr Melsom assess the individual shape and wear of the shoulder and consider implant size and position before the operation.
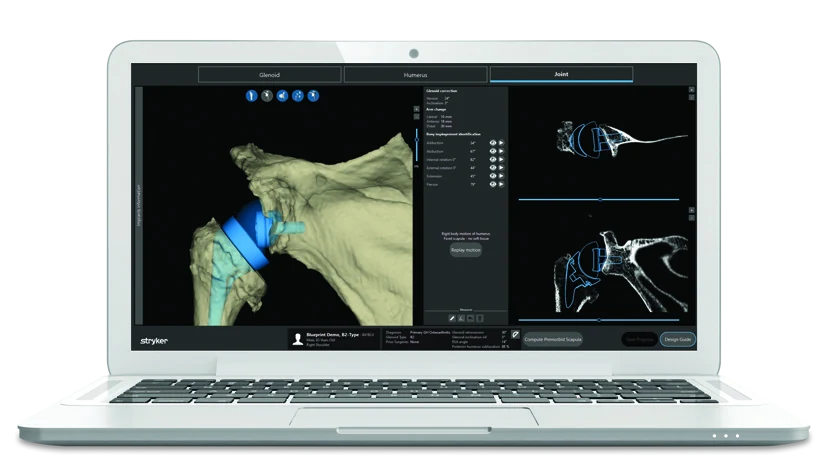
From scan to surgical plan
- CT scan: a suitable scan provides detailed information about the shoulder bones.
- 3D assessment: the software reconstructs the anatomy so the surgeon can assess socket wear, orientation and remaining bone.
- Virtual implant planning: implant options, sizes and positions are evaluated. For an anatomic replacement, this includes planning the socket component; for a reverse replacement, it includes the baseplate supporting the ball on the shoulder blade. The choice of replacement also depends on the clinical assessment and rotator cuff.
- Patient-specific guides, when appropriate: an optional guide is made to fit the patient’s bone and help transfer the planned pin position and direction to surgery. A custom guide does not necessarily mean the implant itself is custom-made. The surgeon checks the guide fit and the anatomy during the operation.
- Surgery and follow-up: the plan supports surgical decisions. Postoperative X-rays show the implanted components, while clinical follow-up and rehabilitation assess recovery, movement and function.
View the total shoulder replacement case series: Blueprint planning, guide design and final X-ray.
View a postoperative reverse shoulder X-ray.
What planning and guides add
Three-dimensional planning helps the surgeon anticipate anatomical challenges and prepare the intended implant position. A patient-specific guide provides a physical way to transfer part of that plan into the operation. Neither replaces surgical judgement or guarantees a particular recovery. Implant position is only one factor: bone quality, soft tissues, healing and rehabilitation also matter.
Blueprint planning and patient-specific guides are distinct from robotic assistance. Read about Mako-assisted shoulder surgery.
About Blueprint planning · Manufacturer information on patient-specific guides.
The surgery and hospital stay
- Performed under general anaesthesia, usually with a nerve block for comfort
- Hospital stay is typically 1–2 nights
- A sling is worn for comfort and protection for the early weeks
Recovery
- Everyday light tasks (eating, writing, keyboard) resume within the first weeks
- Physiotherapy progresses motion and then strength
- Most patients are substantially comfortable by 6–12 weeks, with improvement continuing to 12 months
- Driving is usually possible at around 6 weeks
Outcomes
Modern shoulder replacement is a well-established treatment for shoulder arthritis; for most patients it reduces pain and improves everyday function, with implant survivorship now comparable to hip and knee replacement. Risks — infection, instability, nerve injury and the need for revision over time — are uncommon and will be discussed in detail at your consultation.
Mako robotic-assisted shoulder surgery
Following the initial trial at the Wesley Hospital, Dr Melsom plans to offer Mako-assisted reverse shoulder replacement to suitable patients. Robotic assistance adds guidance during socket preparation to the existing 3D planning process. Read how Mako compares with planning and patient-specific guides, and what the evidence can tell us.